 breva




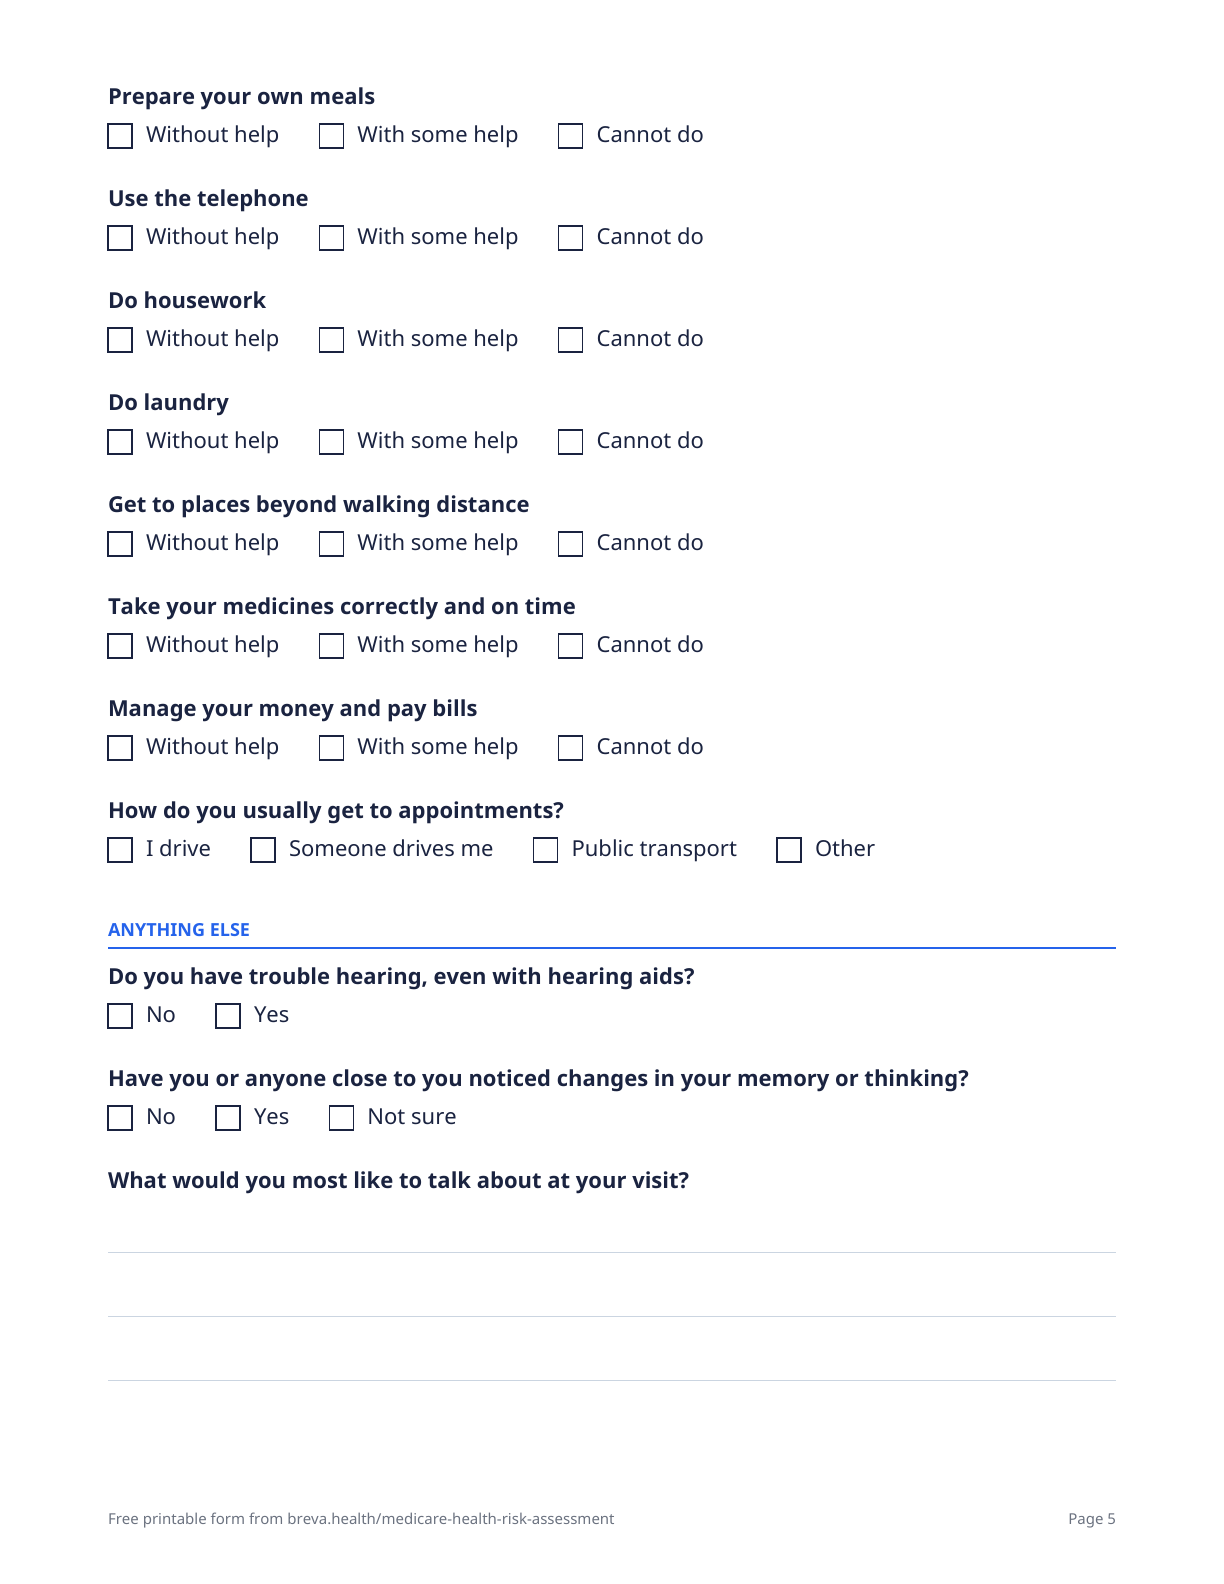
The questions on the form
About you
- Name
- Date of birth
- Today's date
- Gender
- Race and ethnicity, in your own words
- Preferred language
- Who filled in this form?I did / Someone helped me / Someone filled it in for me
Your health
- In general, how would you rate your health?Excellent / Very good / Good / Fair / Poor
- Compared with a year ago, your health isBetter / About the same / Worse
- In the past year, how many times have you stayed overnight in a hospital?None / Once / Two or more times
- Do you feel you have become weaker, slower or more tired over the past year?No / A little / A lot
- Can you walk a quarter of a mile (about two blocks) without stopping?Yes, easily / Yes, with difficulty / No
- Can you climb a flight of stairs without resting?Yes, easily / Yes, with difficulty / No
How you have been feeling
Over the past two weeks:
- How often have you felt down, depressed or hopeless?Not at all / Several days / More than half the days / Nearly every day
- How often have you had little interest or pleasure in doing things?Not at all / Several days / More than half the days / Nearly every day
- How often have you felt stressed, worried or on edge?Not at all / Several days / More than half the days / Nearly every day
- How often have you felt angry or irritable?Not at all / Several days / More than half the days / Nearly every day
- How often have you felt lonely or cut off from other people?Not at all / Several days / More than half the days / Nearly every day
- How much has pain gotten in the way of your daily life?Not at all / A little / Quite a bit / A lot
- How often have you felt too tired to do what you want to do?Not at all / Several days / More than half the days / Nearly every day
Your life
- Overall, how satisfied are you with your life?Very satisfied / Satisfied / Not very satisfied / Not at all satisfied
Your habits and safety
- Do you smoke or use tobacco or nicotine products, including e-cigarettes?Never / I used to / Yes, now
- How many days a week do you drink alcohol?None / 1 or 2 / 3 to 5 / 6 or 7
- On a day you drink, how many drinks do you usually have?I don't drink / 1 / 2 / 3 or 4 / 5 or more
- How many days a week are you physically active for at least 30 minutes (walking, gardening, exercise)?None / 1 or 2 / 3 or 4 / 5 or more
- How many servings of fruit and vegetables do you eat on a typical day? (A serving is about a handful.)None / 1 or 2 / 3 or 4 / 5 or more
- Do you have trouble chewing or swallowing, or pain in your mouth or teeth?No / Yes
- When did you last see a dentist?Within a year / 1 to 2 years ago / More than 2 years ago
- Do you have any questions or concerns about your sexual health?No / Yes / Prefer not to say
- Do you always wear a seat belt in a car?Yes / No
- Do you drive?Yes / No
- Have you fallen in the past year?No / Once / Two or more times
- Are you afraid of falling?No / Yes
- Do you have trouble with your balance or feel unsteady when you walk?No / Sometimes / Often
- Do you have working smoke detectors at home?Yes / No / Not sure
- At home, are your rugs, stairs and lighting safe to walk on?Yes / No / Not sure
- Do you feel safe where you live?Yes / No
Everyday activities
Can you do these on your own?
- Get dressedWithout help / With some help / Cannot do
- EatWithout help / With some help / Cannot do
- Use the toiletWithout help / With some help / Cannot do
- Groom yourself (brush teeth, comb hair)Without help / With some help / Cannot do
- Bathe or showerWithout help / With some help / Cannot do
- Walk across a roomWithout help / With some help / Cannot do
- Get in and out of a bed or chairWithout help / With some help / Cannot do
Running your home
Can you do these on your own?
- Shop for groceries and other things you needWithout help / With some help / Cannot do
- Prepare your own mealsWithout help / With some help / Cannot do
- Use the telephoneWithout help / With some help / Cannot do
- Do houseworkWithout help / With some help / Cannot do
- Do laundryWithout help / With some help / Cannot do
- Get to places beyond walking distanceWithout help / With some help / Cannot do
- Take your medicines correctly and on timeWithout help / With some help / Cannot do
- Manage your money and pay billsWithout help / With some help / Cannot do
- How do you usually get to appointments?I drive / Someone drives me / Public transport / Other
Anything else
- Do you have trouble hearing, even with hearing aids?No / Yes
- Have you or anyone close to you noticed changes in your memory or thinking?No / Yes / Not sure
- What would you most like to talk about at your visit?